The Fine Print of Fast-Track Trials: Decoding a Tanezumab-Style Consent Form Before You Sign It

The Paragraph Most Volunteers Skim
Ask anyone who has enrolled in a clinical trial for an experimental pain therapy what they signed, and most will say 'a consent form.' Ask them what that form said about their joints, and the room goes quiet.
For investigational monoclonal antibodies targeting nerve growth factor — tanezumab being the most publicized example — the informed consent document carries a warning unlike anything in a standard analgesic trial: the possibility of rapid progressive osteoarthritis, a condition in which a joint can deteriorate catastrophically within months. Understanding how that risk is worded, and what it legally commits you to, is the single most important act of self-advocacy a prospective volunteer can perform.
Why 'Documented Joint Destruction' Appears at All
Consent forms are not written to comfort you; they are written to disclose. The phrase 'documented joint destruction' — or close variants like 'radiographically confirmed structural joint damage' — exists because regulators at the FDA required it after Phase III data revealed an imbalance of serious joint events between treated and control groups.
In plain terms, the clause tells you three things:
- The risk is known, not hypothetical. Sponsors cannot use vague boilerplate for a safety signal the agency has already flagged. Expect explicit naming of the adverse event, its observed frequency, and the joint spaces where it appeared most often — hips and knees, in the tanezumab program.
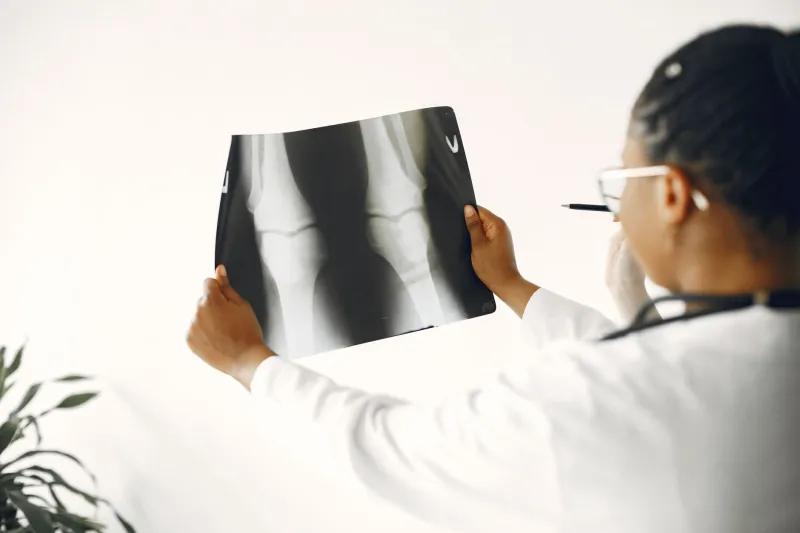
- Detection is defined. The form will describe how investigators monitor for the event, typically through scheduled X-rays or MRI imaging of weight-bearing joints. If a clause promises 'regular joint monitoring,' ask what that means in practice: how often, which joints, and who reads the images.
- Consequences are described, not minimized. Some volunteers in the tanezumab program required total joint replacement. A compliant consent form will not shy away from saying so.
The Clauses That Carry the Most Weight
Not every paragraph deserves equal attention. Based on how these documents are structured under US regulations, four sections do the heaviest lifting.
1. The Risk Summary Versus the Risk Detail
Most consent forms open with a readable summary — often in a boxed format required for certain FDA-regulated trials — followed by exhaustive detail deeper in the document. The summary is legally required to be accurate, but it compresses. The phrase 'possible worsening of existing osteoarthritis' in a summary may correspond to three paragraphs of detail about arthroplasty rates. Read both.
2. The Compensation and Treatment Clause
Here is a truth that surprises many volunteers: trial-related injury care is often covered, but the language rarely promises more than 'reasonable medical care' for injuries caused by the investigational product. It typically does not cover complications of a pre-existing condition — including osteoarthritis that progresses for reasons unrelated to the drug. Because rapid progressive osteoarthritis can be difficult to attribute definitively, this clause determines who pays for a hip replacement if causation is disputed. Read it twice.
3. The Withdrawal Provision
Federal law guarantees your right to leave a trial at any time without penalty. The operative question is what happens to your safety follow-up if you withdraw. Look for language requiring extended joint imaging after discontinuation — some NGF-inhibitor protocols mandated follow-up for months after the last dose, because the antibody's effects persist well beyond the infusion itself.
4. The Alternatives Section
A well-constructed form must describe standard treatments you could receive instead. If the alternatives section reads thin — a sentence about 'usual care' — that is a signal to ask your own physician what the accepted standard would be for your condition. An informed refusal is as important as an informed yes.
What You Can and Cannot Negotiate
You cannot negotiate the science. The risk of joint destruction is what the data says it is, and no conversation with the study coordinator changes the biology. But you can negotiate practical terms:
- Frequency of imaging. If you have a family history of degenerative joint disease, ask whether baseline and interim imaging of your specific problem joints can be added.
- Clarity on follow-up duration. Get the post-treatment monitoring period in writing, in months, not 'per protocol schedule.'
- A second reader. Nothing prevents you from taking the consent document home, or to an independent physician, before signing. A form rushed at the bedside is a form you have not consented to.
The Bottom Line for Prospective Volunteers
The dense language in these documents is not there to confuse you — it is there because regulators learned, expensively, what happens when it is absent. Phrases like 'documented joint destruction' are the residue of real patients and real injuries. Reading a consent form like a pharmacologist does not require a pharmacology degree; it requires the patience to treat every unfamiliar term as a question, and the insistence on getting that question answered before your signature makes the trial possible.